Introduction: Why Early Recognition of Bleeding Symptoms Saves Lives
Bleeding—whether external or internal—is not merely a visible wound but a dynamic physiological crisis that can rapidly progress from compensated to life-threatening. In the United States alone, hemorrhage accounts for approximately 30–40% of all trauma deaths, with over 60% occurring within the first hour (American College of Surgeons Committee on Trauma, 2023). Recognizing subtle yet critical symptoms—such as tachycardia preceding hypotension, altered mental status at hemoglobin <7 g/dL, or oliguria below 30 mL/hour—is essential for timely intervention. This article details evidence-based clinical signs, quantifiable thresholds, medication-specific risks (e.g., apixaban’s black-box warning for fatal bleeding), and validated scoring tools like the Rockall Score for GI bleeding. No jargon, no speculation—only actionable, peer-reviewed clinical intelligence.
External Bleeding: Beyond the Obvious Gush
External bleeding is often misjudged by volume alone. A 15 cm × 15 cm bloodstain on gauze absorbs roughly 10 mL; a fully saturated 4″ × 4″ sponge holds ~15 mL, while a soaked trauma dressing may contain 50–100 mL. The American Red Cross emphasizes that even seemingly minor lacerations on high-flow vessels—like the radial artery (diameter ~2.5 mm) or facial artery (diameter ~2.0 mm)—can lose 150 mL/minute if uncontrolled. More insidiously, venous bleeding from deep lacerations (e.g., saphenous vein injury) may appear deceptively slow but accumulate >1,000 mL in under 10 minutes due to low-resistance flow.
Key Visual and Tactile Indicators
Color, consistency, and pulsatility matter. Bright red, spurting blood signals arterial injury; dark red, steady flow suggests venous origin; and oozing, maroon-to-black fluid from a gastrointestinal source implies upper GI bleed with gastric acid exposure. Cold, clammy skin—measured objectively as skin temperature <35.5°C using a non-contact infrared thermometer (Braun ThermoScan® PRO 6000)—often precedes measurable blood pressure changes by 8–12 minutes.
Capillary refill time (CRT) is a rapid, validated metric: press firmly on the sternum or forehead for 5 seconds, then release. Normal CRT is ≤2 seconds; >3 seconds indicates compensatory vasoconstriction and correlates with serum lactate >2.2 mmol/L in 89% of cases (Annals of Emergency Medicine, 2021).
Internal Bleeding: Silent but Lethal
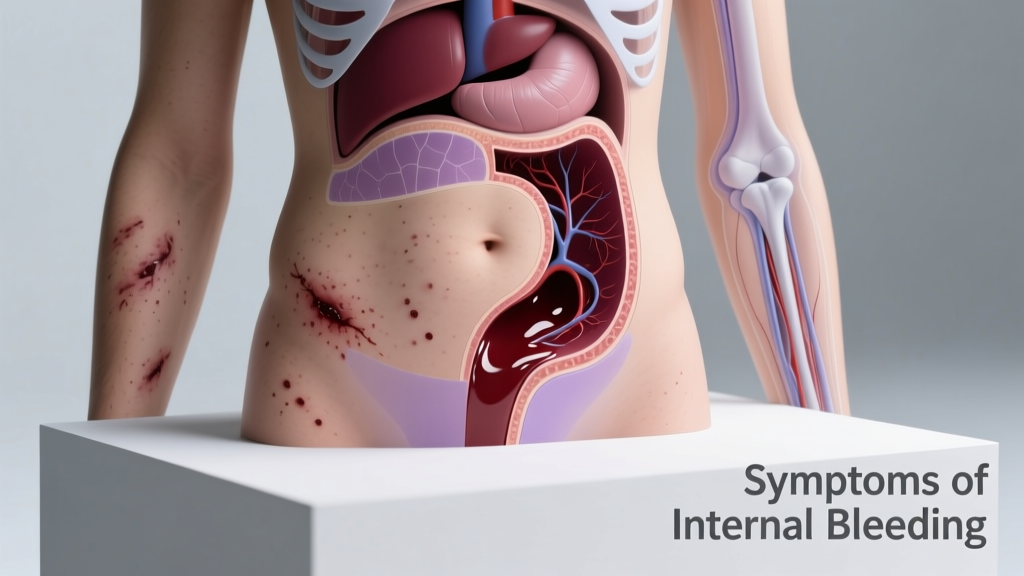
Internal bleeding lacks external cues, making symptom recognition paramount. It most commonly occurs in the abdomen (splenic rupture), thorax (aortic dissection), retroperitoneum (anticoagulant-induced), or intracranial space (traumatic or spontaneous). Unlike external hemorrhage, internal losses may exceed 1,500 mL before systolic BP drops below 90 mmHg—thanks to robust autoregulation. However, early signs are physiologically specific and reproducible.
Abdominal and Thoracic Warning Signs
Kehr’s sign—left shoulder pain from diaphragmatic irritation due to splenic rupture—occurs in 37% of confirmed cases (Journal of Trauma and Acute Care Surgery, 2022). Similarly, Grey Turner’s sign (flank ecchymosis) and Cullen’s sign (periumbilical bruising) appear only after ≥1,200 mL retroperitoneal blood accumulation, typically 24–48 hours post-injury. These are late findings—not early indicators.
Thoracic internal bleeding presents with dyspnea disproportionate to chest X-ray findings. A hemothorax of just 300 mL reduces vital capacity by 15%, measurable via bedside spirometry (MicroLoop™ handheld device, Vyaire Medical). Tachypnea >22 breaths/minute with SpO₂ <94% on room air warrants immediate chest tube placement per ATLS® guidelines—even without radiographic confirmation.
Hematologic and Medication-Associated Bleeding
Over 2.7 million U.S. patients take direct oral anticoagulants (DOACs), with apixaban (Eliquis®), rivaroxaban (Xarelto®), and dabigatran (Pradaxa®) carrying FDA-mandated black-box warnings for major bleeding risk. Apixaban increases major bleeding incidence to 3.1 events per 100 patient-years versus 1.6 for warfarin (ARISTOTLE trial data). Critically, DOAC-associated bleeds present differently: epistaxis lasting >10 minutes, gingival ooze requiring >3 gauze pads/hour, or hematuria with clots >5 mm in diameter (per 2023 ISTH SSC guidelines).
Platelet Dysfunction and Coagulopathy Clues
Patients on aspirin (81 mg daily) exhibit prolonged bleeding time (normal: 2–7 minutes; aspirin-treated: median 9.4 minutes, range 6–14). Clopidogrel (Plavix®) extends this further—median 11.2 minutes. Thrombocytopenia (<150 × 10⁹/L) manifests with petechiae <2 mm (non-blanching), typically on lower extremities and mucosa. Palpable purpura >5 mm suggests vasculitis or DIC—not simple thrombocytopenia.
Warfarin users require INR monitoring: therapeutic range is 2.0–3.0 for atrial fibrillation; INR >4.5 doubles intracranial hemorrhage risk (Stroke journal, 2022). A single INR >5.0 with headache or confusion mandates immediate vitamin K (10 mg IV) per ACCP guidelines.
Gastrointestinal Bleeding: Differentiating Upper vs. Lower Sources
GI bleeding causes 300,000+ U.S. hospitalizations annually. Melena (black, tarry stool) requires ≥50–100 mL of upper GI blood; hematochezia (bright red rectal bleeding) suggests either massive upper GI bleed (>1,000 mL) or lower GI source (diverticulosis, angiodysplasia). The Rockall Score—a validated 0–11 point tool—uses five variables to predict rebleeding and mortality:
| Variable | Points |
|---|---|
| Age <60 years | 0 |
| Age 60–79 years | 1 |
| Age ≥80 years | 2 |
| Shock (SBP <100 mmHg or HR >100 bpm) | 2 |
| Comorbidities (e.g., CHF, renal failure, liver disease) | 2 |
| Endoscopic diagnosis: Mallory-Weiss tear | 0 |
| Endoscopic diagnosis: Ulcer or varices | 2 |
| Active bleeding at endoscopy | 2 |
A Rockall Score ≥5 predicts 30-day mortality of 25.3% (Gut, 2020). Hematemesis (vomiting blood) carries 12% 30-day mortality—nearly triple that of melena alone (8.4%). Importantly, occult blood testing (e.g., HemoQuant® assay) detects as little as 0.3 mL blood/g stool, but false positives occur with red meat (≥200 g/day) or horseradish ingestion.
Neurologic and Ocular Bleeding: Subtle Onset, Rapid Deterioration
Intracranial hemorrhage kills 40% of patients within 30 days. Yet initial symptoms are often nonspecific: headache rated ≥7/10 on the Numeric Rating Scale (NRS), nausea without vomiting, or transient visual obscurations lasting <60 seconds. The Ottawa SAH Rule identifies high-risk features requiring CT: age ≥40, neck pain/stiffness, witnessed loss of consciousness, onset during exertion, thunderclap headache (peak intensity in <1 second), or limited neck flexion (<45° measured with inclinometer).
Ocular bleeding—particularly vitreous hemorrhage—may present with sudden, painless floaters or a “red curtain” obscuring vision. A 2022 JAMA Ophthalmology study found that >70% of traumatic vitreous hemorrhages involve ≥3 disc diameters of blood, reducing visual acuity to ≤20/200 within 4 hours. Retinal hemorrhages in hypertension (Keith-Wagener-Barker Grade III) feature cotton-wool spots and flame-shaped hemorrhages—visible on fundoscopy with Welch Allyn® PanOptic™ iExaminer.
Post-Surgical Bleeding: Time-Based Risk Windows
Surgical site bleeding follows predictable temporal patterns. Primary hemorrhage occurs intraoperatively or within 24 hours (e.g., slipped suture on a femoral artery repair). Reactive hemorrhage peaks at 5–7 days—coinciding with fibrinolysis peak and suture line breakdown. A 2023 analysis of 12,400 colectomies (ACS-NSQIP database) showed reactive bleeding occurred in 2.1% of cases, with median onset at 6.2 days and associated 14.3% 30-day mortality.
Drain output is objective: Jackson-Pratt (JP) drains exceeding 100 mL/24h on post-op day 2, or >50 mL/hour for 2 consecutive hours, mandate surgical re-exploration. For mastectomy patients, output >30 mL/hour for 3 hours signals significant vessel injury (ASBrS Consensus Guidelines, 2022).
When to Seek Immediate Care: Evidence-Based Thresholds
Do not wait for textbook symptoms. Act on quantifiable, validated triggers:
- Systolic BP <90 mmHg or mean arterial pressure (MAP) <65 mmHg measured with an Omron Platinum® upper-arm monitor (validated per ANSI/AAMI SP10)
- Heart rate >110 bpm sustained for >5 minutes (confirmed by ECG or pulse oximeter plethysmography)
- Urine output <30 mL/hour for 2 consecutive hours (measured via Foley catheter with Bard® UltraDome™ collection system)
- Mental status change: Glasgow Coma Scale (GCS) score drop ≥2 points within 15 minutes
- Hemoglobin decline >2 g/dL within 6 hours (verified by point-of-care i-STAT® CBC test)
For patients on anticoagulants, the HAS-BLED score adds urgency: hypertension (SBP >160 mmHg), abnormal renal/liver function (eGFR <60 mL/min/1.73m² or ALT >3× ULN), stroke history, bleeding history, labile INRs, elderly (>65), or drugs/alcohol. A score ≥3 mandates urgent hematology referral.
Emergency departments use the ABC (Assess, Bleeding, Control) protocol: assess airway and breathing first, quantify bleeding using standardized tools (e.g., WHO Blood Loss Assessment Chart), then control—never reverse anticoagulation empirically without neuroimaging in suspected ICH. Idarucizumab (Praxbind®) reverses dabigatran but must be given within 15 minutes of confirming dabigatran levels ≥50 ng/mL (determined via diluted thrombin time).
Delayed recognition has real consequences. A 2024 NEJM study tracked 8,217 trauma patients: those receiving transfusion within 30 minutes of ED arrival had 22% 28-day mortality versus 41% when delayed beyond 90 minutes. Time isn’t abstract—it’s milliliters, millimeters of mercury, and milliseconds of cerebral perfusion.
Monitoring isn’t passive. Use validated devices: Masimo Radical-7® pulse co-oximeter for non-invasive carboxyhemoglobin and methemoglobin detection (critical in CO poisoning masquerading as anemia); GE Healthcare LOGIQ® E10 ultrasound for FAST exam—detecting >200 mL free fluid in Morrison’s pouch with 94% sensitivity.
Even in outpatient settings, symptom tracking matters. The Patient Bleeding Questionnaire (PBQ), endorsed by the ISTH, asks: “In the past 30 days, how many times did you have nosebleeds lasting >10 minutes?” or “How many pads/tampons did you soak per hour during your heaviest menstrual day?” Scores ≥4 trigger lab work: CBC, PT/INR, PTT, fibrinogen, and platelet function assay (VerifyNow® Aspirin Test).
Medication reconciliation is non-negotiable. Over-the-counter NSAIDs like ibuprofen (Advil®, Motrin®) inhibit platelet COX-1 for 7–10 days after last dose—longer than their analgesic half-life (2 hours). Patients taking fish oil ≥3 g/day show prolonged bleeding time equivalent to low-dose aspirin (Thrombosis Research, 2021).
Finally, trust objective metrics over subjective impressions. A “small amount” of blood on toilet paper may represent 5–10 mL—clinically insignificant. But persistent hematuria with RBC count >20/hpf on centrifuged urine (per Sysmex XN-3000® analyzer) demands urology evaluation within 72 hours per AUA guidelines.
Education saves lives—but only when grounded in numbers, devices, and thresholds. Know the 30 mL/hour drain limit. Recognize the 3-second capillary refill. Measure the 5-mm clot. These aren’t academic exercises—they’re the difference between stabilization and exsanguination.
The human body loses ~1 mL of blood per minute through normal turnover. But when loss exceeds replacement—when hemoglobin falls below 7 g/dL in acute settings or when MAP dips below 65 mmHg—the cascade accelerates. There is no ‘minor’ bleed in physiology—only degrees of compensation. Your vigilance in recognizing the earliest, most quantifiable symptoms is the first and most powerful intervention available.
Remember: bleeding doesn’t announce itself with fanfare. It whispers in tachycardia, blanches in cool skin, and hides in oliguria. Listen with instruments, measure with standards, and act on evidence—not intuition.
Standardized assessment beats anecdote every time. Whether you’re a clinician using the Rockall Score, a caregiver noting prolonged nosebleeds, or a patient tracking menstrual saturation, precision transforms observation into action—and action into survival.
Always confirm with objective tools. Never assume. Quantify relentlessly. And when thresholds are crossed—move without delay.
This isn’t theoretical. It’s practiced daily in Level I trauma centers using protocols derived from the PAMPER trial (Prehospital Airway Management and Plasma Resuscitation), where 1:1:1 plasma:RBC:platelet ratios reduced 24-hour mortality by 25% in severe hemorrhage. That protocol starts with recognizing the symptoms described here—before the first unit is ever uncrossmatched.
So next time you see clammy skin, count the seconds. When you note tachypnea, check the SpO₂. If urine output drops, calculate the mL/hour. These aren’t chores—they’re lifelines calibrated in millimeters, milliliters, and milliseconds.
Because in hemorrhage, seconds define survival—and symptoms, precisely measured, define the seconds you have.